Genetic Testing

A blood or saliva test that reads inherited DNA variants — it estimates future risk instead of measuring what is happening now, and starts with family history.

Last updated October 2026 · New Dawn Health editorial team

What it measures
Inherited DNA variants tied to disease risk
Sample
Blood or saliva — no radiation
Result
A risk estimate, not a diagnosis
Where it fits
After a family-history risk assessment

What is genetic testing?

Genetic testing examines your DNA for inherited variants — changes passed down through families — that raise your lifetime risk of specific diseases. It is most established for cancer-predisposition genes: BRCA1 and BRCA2, linked to breast and ovarian cancer, and the Lynch syndrome genes, linked to colorectal cancer. Unlike almost every other screen in this wiki, it does not measure what is happening in your body today. It reads the instructions you were born with and estimates probability.
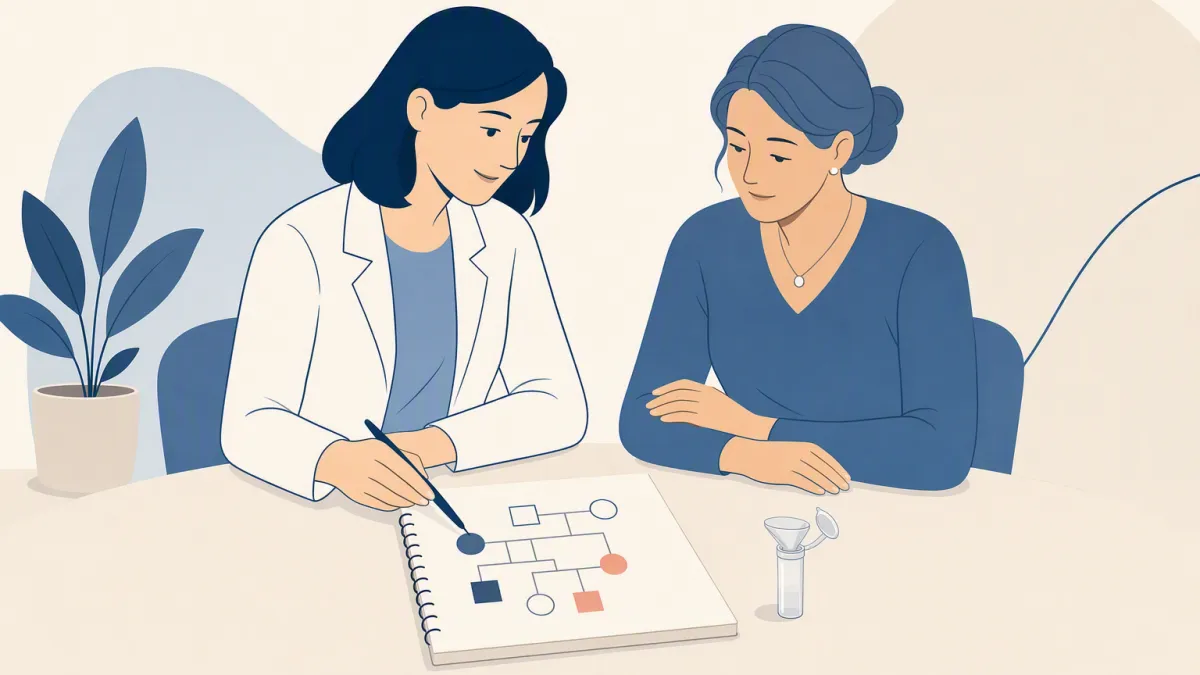
A genetic counselor sketches a family-tree diagram with a patient, a saliva collection kit on the table between them.
The family tree decides whether testing is worth doing at all.

What it finds

Genetic testing finds inherited variants that shift your baseline risk, and the best-validated ones sit in cancer-predisposition genes. These findings rarely change what is true today; they change the plan:

Two well-studied hereditary cancer syndromes and what a result changes.
Genes Raises the risk of What a positive result can change
BRCA1, BRCA2 Breast and ovarian cancer Earlier breast screening, with MRI added to mammography (American Cancer Society) — see breast imaging
Lynch syndrome genes Colorectal and endometrial cancer Earlier and more frequent colonoscopy, set by a specialist

Genetics sets the schedule; imaging and endoscopy do the looking.

What it can't tell you

Most people who test do not carry a high-risk variant, and a negative result does not mean zero risk. Limits worth understanding before you order the test:

  • Common cancers still occur in people who test negative, because most are not inherited.
  • A negative result for a variant already known in your family is a true negative for that variant. With no known family variant, a negative result is uninformative, and risk from your family history is unchanged.
  • Neither kind of negative says anything about non-inherited disease.
  • Many findings are variants of uncertain significance — DNA changes that cannot yet be tied to disease and should not guide action. Some are reclassified later.
  • A broad panel can return more than you came for. Decide with the counselor beforehand how much you want to know.
  • Privacy differs by country. In the US, GINA (2008) bars genetic discrimination in health insurance and employment but not in life, disability or long-term care insurance. Check the rules where you live before you test.

Because results carry psychological weight and affect blood relatives, genetic counseling before and after testing is recommended (CDC). Ask your coordinator how counseling is arranged for your screening plan.

Where it fits in screening

  1. 1
    Family history first
    A clinician uses a brief risk-assessment tool built on your personal and family history.
  2. 2
    Counseling before the test
    If the tool flags raised risk, a genetic counselor helps choose the right test — often starting with a relative who has had cancer.
  3. 3
    The test
    A blood or saliva sample, analyzed for the chosen genes.
  4. 4
    Counseling after the result
    Positive, negative or uncertain, the counselor explains what it means for you and your relatives, and what screening changes.

Sources & further reading

  1. [1] Genetic testing for inherited cancer risk — fact sheet (counseling, panels, VUS, consent, HIPAA and GINA) — National Cancer Institute
  2. [2] BRCA-related cancer: risk assessment, genetic counseling, and genetic testing (2019) — US Preventive Services Task Force
  3. [3] Genetic testing — counseling before and after — US Centers for Disease Control and Prevention
  4. [4] ACS recommendations for the early detection of breast cancer — MRI for high-risk women — American Cancer Society
  5. [5] Genetic discrimination — what GINA does and does not cover — NIH / National Human Genome Research Institute

Genetic Testing — Frequently Asked Questions

Does genetic testing tell me I have cancer?

No. Genetic testing reports risk, not current disease. A pathogenic BRCA or Lynch variant means a higher lifetime probability of a specific cancer and usually calls for earlier, more intensive screening — not a diagnosis. Imaging, endoscopy, and bloodwork are what confirm whether disease is actually present today.

What does a negative result mean?

It depends on what was tested. Not carrying a variant already known in your family is a true negative for that variant. With no known family variant, a negative result is uninformative, and risk from your family history is unchanged. Most cancers are not inherited, so standard age-based screening still applies. A variant of uncertain significance is not a negative result either; it is a change science cannot yet interpret.

Should I get genetic counseling?

Yes — before and after testing. Results affect blood relatives and carry psychological weight, so a counselor helps choose the right test and explains what a result means for you and your family.

Should everyone have genetic testing?

No. The US Preventive Services Task Force recommends BRCA risk assessment for women with a relevant personal or family history or ancestry, then counseling and testing if indicated. It recommends against routine risk assessment, genetic counseling, or genetic testing for women without that history.

Screen smart. Travel once. Know where you stand.

Compare screening packages, see exactly what each one includes, or talk to a coordinator about fitting Genetic Testing into your visit to Taiwan.