What is screening bloodwork?
Screening bloodwork is the chemistry layer of a health check: one needle draw, many separate lab tests. There is no single standard panel — the tests depend on the package and on your age, history and risk. Every value is read against a reference range, so the result is a number rather than an impression. Common tests include:
- Complete blood count — red cells, white cells and platelets
- Glucose and HbA1c — blood sugar now, and over about three months
- Lipids — cholesterol and triglycerides
- Kidney and liver markers — how those organs are working
- Thyroid (TSH), when there is a reason — US guidance finds the evidence insufficient for routine thyroid screening without symptoms (see hormone tests)
How bloodwork works
-
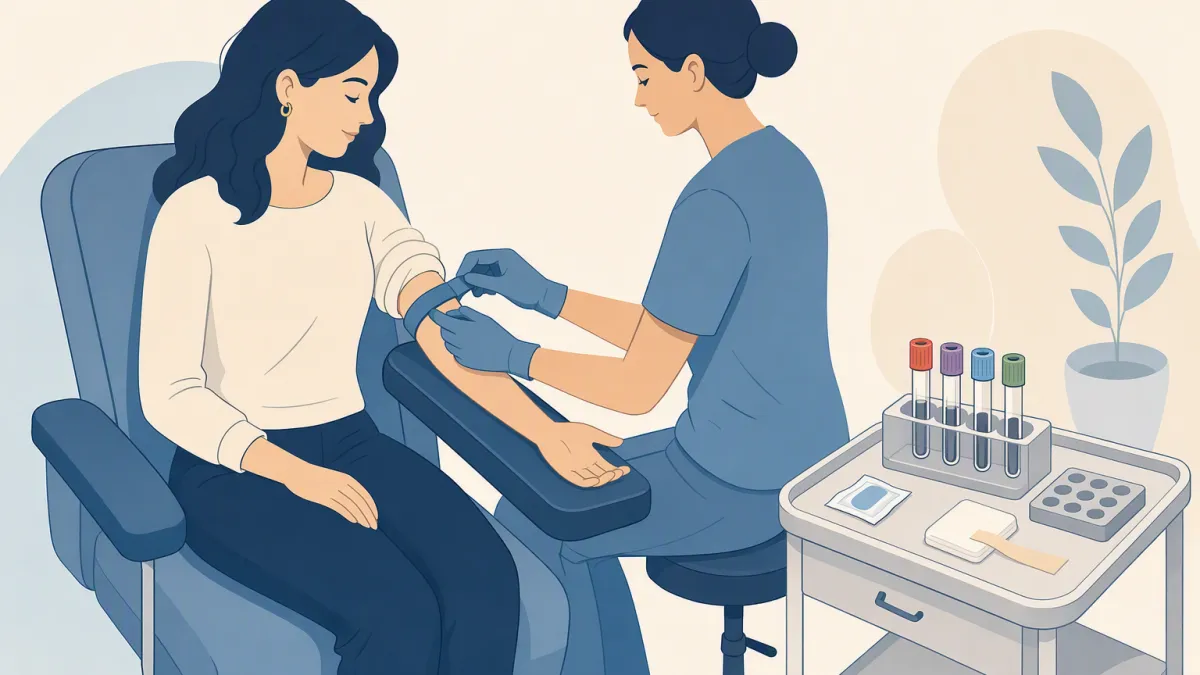
1A needle in a veinThe needle goes into a vein in the crook of your elbow. Veins sit close to the surface and run at low pressure, which is why they are used rather than arteries.
-
2The tubes fill themselvesEach tube is sealed under vacuum, so blood is drawn in without anyone pulling on anything.
-
3Several tubes, several colorsDifferent tests need the blood treated differently. The colored cap tells the lab which additive is inside — some keep the sample liquid, others let it clot on purpose.
-
4Pressure, a bandage, and doneThe draw takes a few minutes. Press on the spot for a short while so it does not bruise.
What happens to the tube after it leaves your arm
Most tubes go into a centrifuge, a machine that spins them fast so heavier contents are pushed to the bottom. Blood cells are denser than the fluid they float in, so they pack into the base and leave a clear, straw-colored layer on top: plasma, or serum once clotting proteins are used up. Most chemistry is measured in that clear layer. The complete blood count needs the cells, so that tube is never spun.
An analyzer needs only a few drops per test, which is how one draw yields many results. Most tests come down to one of three mechanisms:
- A chemical reaction. Reagents react with one substance and change the color of the mixture. The machine shines light through the sample: less light getting through means more of the substance.
- Antibody binding. For hormones and other very specific targets, antibodies shaped to latch onto one molecule carry a tag that gives off light when they bind. The amount of light is the measurement.
- Counting. For the complete blood count, cells stream single file through a narrow channel and are counted and sized one by one. The report gives each as a count per unit of blood, alongside measures such as hemoglobin concentration.
Why a reference range is a range, not a line
This is one of the most useful things to understand about a blood result. A reference range is not a boundary between healthy and sick. It is a description of a crowd. For many tests, the range covers the middle 95% of results from a large group of healthy people.
That definition forces something to be true: about 1 in 20 perfectly healthy people fall outside the range by design. Nothing is wrong with them; a range built to hold 95% of a healthy crowd leaves 5% of that crowd outside. So a long panel run on a well person quite often flags one value, and a result just past the edge is a weaker signal than one far outside it.
Ranges are also local. They shift with the lab's method, and often with age and sex. Read a value against the range printed on your own report, not one from a different lab. A normal result is not a guarantee of health either, which is why results are read with the rest of the picture.
Why fasting matters for some tests and not others
Food moves some results directly. Glucose rises after you eat, because that is what eating does, so a fasting glucose is only comparable to its range if you have not eaten. Other tests barely move with a meal. Fasting is therefore test-specific:
| Test | Fasting | Source |
|---|---|---|
| Fasting glucose | At least 8 hours without food | NIDDK |
| HbA1c | No fasting needed — it reflects about three months of blood sugar | NIDDK |
| Lipids (cholesterol) | Non-fasting is accepted for most people; repeat fasting if triglycerides are above 400 mg/dL | ACC/AHA 2026 (US) |
Plain water is usually fine. Your coordinator confirms the rules for your tests when you book. Bloodwork has almost no exclusions, but tell the team:
- If you take a blood thinner or bruise easily, so pressure is held longer
- If needles have ever made you faint, so you can lie down for the draw
- If you take insulin or other diabetes medicines, before you fast
- If you take biotin supplements, which the FDA warns can distort some lab tests
What bloodwork can find
Some common conditions stay silent for years and may first show up as a number drifting outside its range. Depending on the tests ordered, a draw can point to:
- Diabetes and prediabetes — fasting glucose and HbA1c, normally confirmed with a repeat or second test
- High cholesterol — the lipid panel
- Anemia and some blood disorders — the complete blood count
- Kidney and liver problems — the organ markers
- Thyroid imbalance — an out-of-range TSH, when thyroid tests are ordered for a reason (USPSTF finds routine screening evidence insufficient)
What bloodwork does — and does not — do
- Blood sugar, cholesterol, blood cells, and organ and thyroid function, as numbers
- Change over time, when the same tests are repeated
- Plaque in the arteries. A lipid panel gives cholesterol, not hardened plaque; a heart calcium score measures that.
- The structure of organs. A liver marker cannot show a cyst or a stone; an abdominal ultrasound images them.
- Whether you have cancer. Screens with evidence are organ-specific, such as a stool test or colonoscopy, mammography, or a low-dose lung CT for people who qualify.
Where bloodwork fits in a screening
Bloodwork is the objective baseline the rest of a screening is built around. For each test in detail — what it measures and how its result is read — see the comprehensive blood panel page. At New Dawn Health in Taipei, what happens after the draw:
- A report listing each value next to its reference range. Which tests, the report language and turnaround are confirmed when you book.
- A flagged value is checked, not assumed. A repeat test or the trend over time usually comes before any conclusion.
- Results are read with your history. Your coordinator confirms who reviews the report when you book. Take it to your own doctor too, so the numbers join your long-term record.